When Should You See a Pain Management Physician?
Written by YiQiu Hu, NMD
Arizona-licensed naturopathic physician and virtual concierge medicine provider
Published August 2026 | Medically reviewed August 2026
Pain is one of the most common reasons people seek medical care, but deciding when pain warrants a more focused medical evaluation is not always straightforward. Some aches and minor injuries improve with time, activity modification, and conservative care. Other symptoms persist, repeatedly return, interfere with daily activities, or suggest that the underlying source of the pain has not yet been identified.
You do not necessarily need to wait until pain becomes severe or lasts for months before asking for help.
A pain management evaluation may be appropriate when pain is persistent, recurrent, difficult to explain, interfering with function, or not improving as expected. The goal of an evaluation should not simply be to select a medication or procedure. It should be to understand what may be causing the pain, determine whether additional investigation is needed, and develop an appropriate treatment strategy.
At Ask Dr. Hu, our approach to integrative pain management begins with evaluation before treatment. Depending on the condition, care may involve conservative treatment, rehabilitation, complementary therapies, diagnostic ultrasound, targeted procedures, or referral to another medical professional when appropriate.
What Does a Pain Management Physician Do?
Pain management is broader than simply treating a pain score.
Pain may originate from muscles, tendons, ligaments, joints, nerves, the spine, inflammatory conditions, previous injuries, repetitive stress, or multiple contributing factors at the same time. Chronic pain can also become increasingly complex as sleep, movement, physical conditioning, mood, stress, and nervous-system sensitivity interact with the original problem.
For this reason, modern pain care is often multimodal and multidisciplinary, incorporating medical evaluation, rehabilitation, medications when appropriate, procedures, physical or occupational therapy, behavioral strategies, and other treatments according to the patient's needs.
The exact role of a pain management physician depends on the clinician's training, licensure, and practice setting. However, the evaluation commonly focuses on several questions:
What is the likely source of the pain?
Is there evidence of a muscle, tendon, ligament, joint, nerve, or spinal problem?
Is additional imaging or testing actually necessary?
Which treatments have already been attempted?
How is the pain affecting movement, sleep, work, exercise, and everyday activities?
Are there medical conditions or medications that affect treatment selection?
Can the problem reasonably be managed conservatively?
Would a targeted procedure be appropriate?
Does another specialist need to be involved?
If you are new to this type of care, our complete guide to integrative pain management explains how evaluation, rehabilitation, conservative treatments, procedures, and complementary approaches may fit together.
Signs It May Be Time to See a Pain Management Physician
There is no single number on a pain scale or exact timeline that determines when everyone should seek a pain-management evaluation.
The pattern of symptoms and their effect on your life often matter just as much as the intensity of the pain.
1. Your Pain Is Not Improving as Expected
Many minor musculoskeletal injuries improve gradually. If an injury or painful condition continues longer than expected, stops improving, or repeatedly becomes aggravated when you try to return to normal activity, further evaluation may be reasonable.
Persistent symptoms do not automatically mean that something serious is wrong. However, they may indicate that the original diagnosis needs to be reconsidered, rehabilitation needs to be modified, or an underlying structural or neurological contributor has not been adequately addressed.
The CDC generally categorizes pain lasting longer than three months as chronic pain, but you do not need to wait three months to seek evaluation when symptoms are interfering with function or recovery is not progressing appropriately.
2. The Pain Keeps Coming Back
Recurring pain deserves attention even if it temporarily disappears between episodes.
For example, a shoulder may improve with rest but begin hurting every time you return to weight training. Knee pain may repeatedly flare after running. Low-back pain may resolve for several weeks and then return whenever activity increases.
Patterns like these may indicate that treatment has reduced symptoms without fully addressing the factors contributing to recurrence.
An evaluation may help determine whether the problem involves tissue irritation, weakness, movement mechanics, repetitive loading, nerve irritation, arthritis, instability, or another factor.
3. Pain Is Limiting Your Normal Activities
One of the most important reasons to seek evaluation is loss of function.
Consider medical evaluation when pain is preventing you from:
Walking comfortably
Exercising
Sleeping normally
Working
Lifting or carrying objects
Climbing stairs
Driving
Participating in sports
Performing household activities
Caring for children or family members
Returning to normal activities after an injury
Pain does not have to be a 9 out of 10 to matter. Chronic pain that consistently limits work or daily activities is often described as high-impact chronic pain, emphasizing that the effect of pain on a person's life is an important part of clinical assessment.
4. You Still Do Not Know What Is Causing the Pain
Sometimes patients receive several different explanations for the same symptoms.
Shoulder pain, for example, can originate from the rotator cuff, bursa, joint, biceps tendon, cervical spine, muscle, or a nerve. Pain around the knee may arise from several different structures even though the discomfort feels similar.
This is why effective treatment should begin with the most likely diagnosis rather than the treatment someone wants to perform.
A detailed history and physical examination may be enough in some cases. Other situations may require X-rays, MRI, laboratory testing, electrodiagnostic testing, or diagnostic musculoskeletal ultrasound.
Imaging should not automatically be ordered for every painful condition. For common problems such as uncomplicated low-back pain, unnecessary imaging may reveal incidental abnormalities that are not actually causing the symptoms and can lead to additional testing or treatment that provides little benefit.
5. Conservative Treatment Has Not Been Enough
Many musculoskeletal conditions should initially be treated conservatively.
Depending on the diagnosis, this may include:
Temporary activity modification
Progressive exercise
Physical therapy
Mobility work
Strengthening
Ergonomic changes
Heat or cold
Appropriate nonprescription or prescription medications
Acupuncture
Other noninvasive treatments
Major clinical guidelines support nonpharmacologic and nonopioid approaches for many common painful conditions before escalating treatment when clinically appropriate.
If you have already tried appropriate conservative treatment and remain significantly limited, a pain-management evaluation may help determine why treatment has not worked and whether another approach should be considered.
That does not automatically mean an injection is the next step.
Sometimes the answer is better rehabilitation. Sometimes a diagnosis needs to be reconsidered. Sometimes additional imaging is appropriate. And in selected cases, a targeted procedure may be reasonable.
6. You Are Relying Increasingly on Pain Medication
Medication can be an appropriate component of pain treatment, but increasing reliance on medication without understanding or addressing the underlying condition is a reason to reassess the overall treatment plan.
This is particularly important when medications are providing only short-lived benefit, requiring progressively greater use, causing side effects, or allowing symptoms to continue without meaningful improvement in function.
The CDC recommends maximizing appropriate nonpharmacologic and nonopioid treatments for many patients with subacute and chronic pain and considering the expected effects on both pain and function when treatment decisions are made.
A broader pain-management plan may incorporate rehabilitation, physical treatment, lifestyle strategies, appropriate medications, and selected procedures rather than relying exclusively on one intervention.
7. You Have Persistent Numbness, Tingling, or Nerve-Like Pain
Burning, electrical, shooting, tingling, or radiating pain may suggest that a nerve is involved.
Examples include symptoms traveling down an arm or leg, numbness in part of the hand or foot, or pain following the distribution of a peripheral nerve.
Persistent neurological symptoms should be medically evaluated because treatment depends on where and why the nerve is being affected.
Importantly, slowly developing or stable nerve symptoms are different from sudden neurological deficits. Sudden weakness, paralysis, loss of bowel or bladder control, or numbness in the groin or saddle region requires urgent medical evaluation rather than a routine pain-management appointment.
8. You Are Considering an Injection or Other Procedure
An injection should follow a diagnosis—not substitute for one.
Before performing a joint injection, nerve block, trigger-point injection, regenerative procedure, or other intervention, the physician should understand the suspected pain-generating structure and explain why the proposed treatment makes sense for your condition.
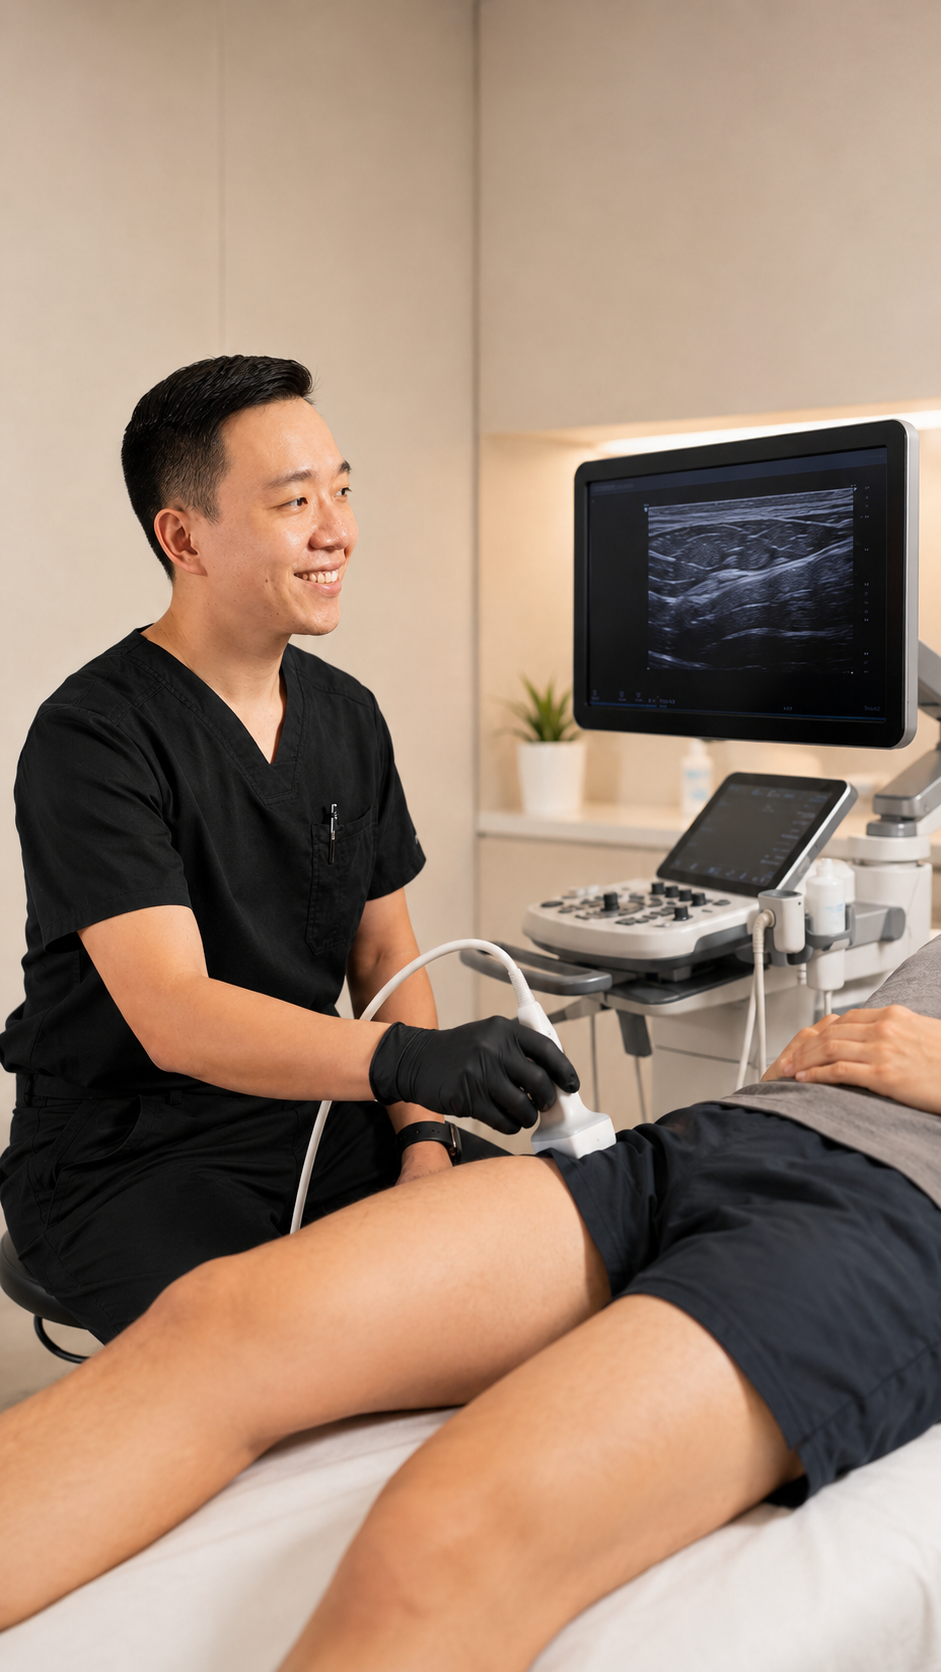
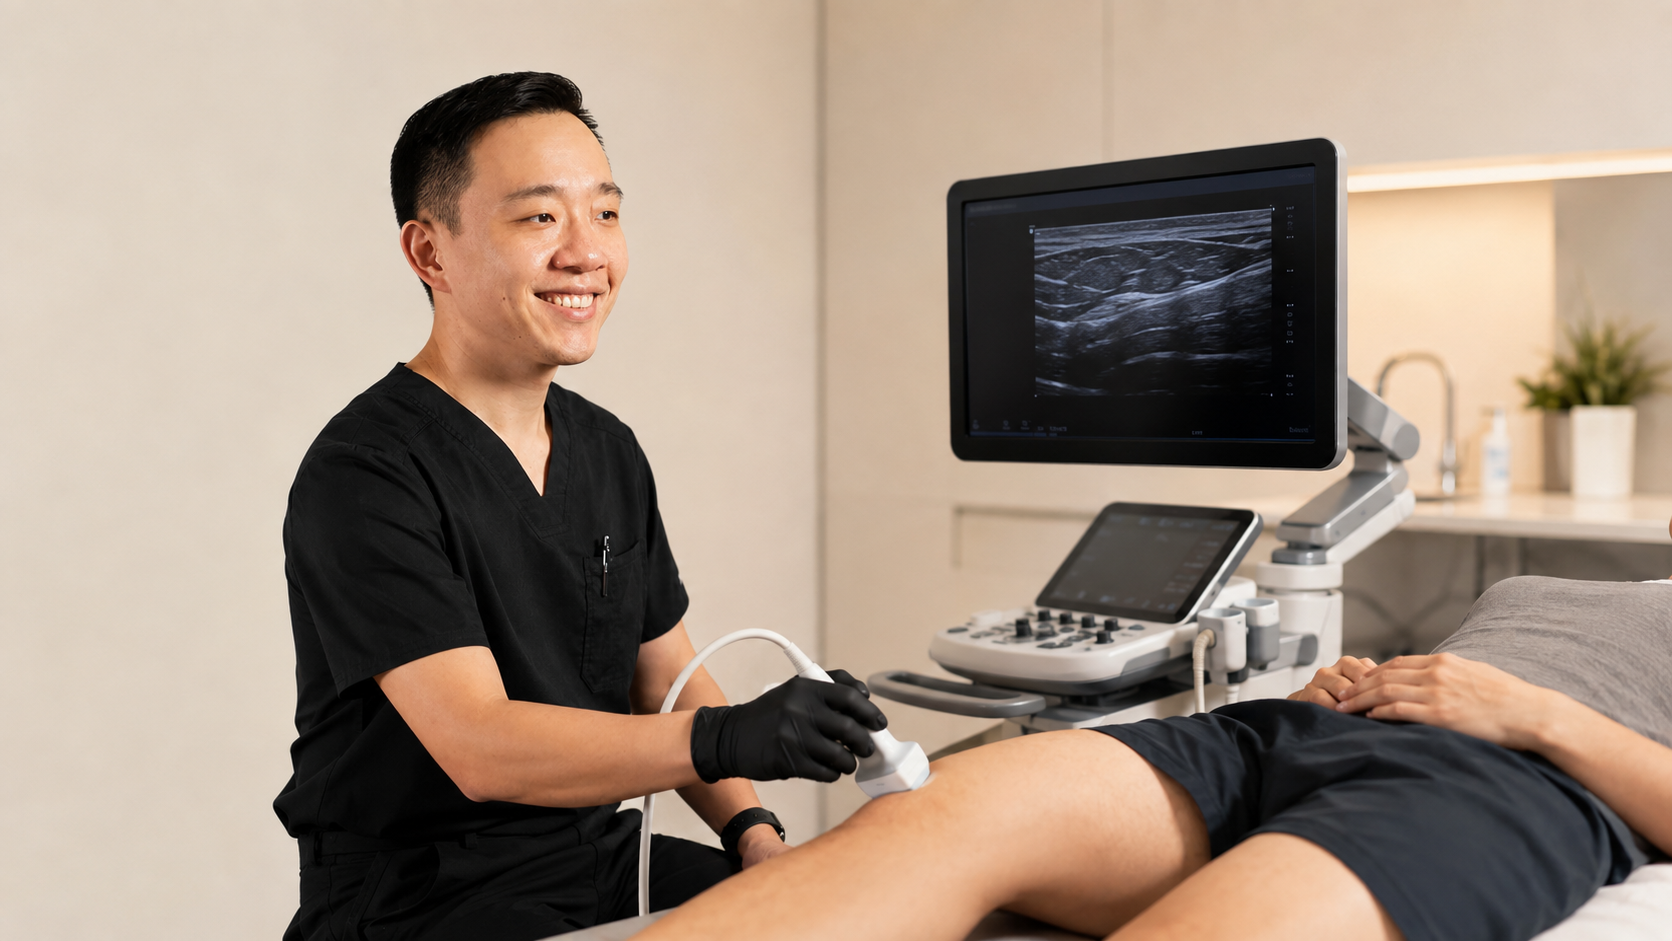
In selected situations, musculoskeletal ultrasound can help visualize muscles, tendons, joints, nerves, blood vessels, and other anatomy during evaluation or procedural planning. Ultrasound guidance may also allow real-time visualization of needle placement during certain injections.
Not every patient needs a procedure, and not every procedure requires ultrasound.
9. Pain Is Affecting Your Sleep, Mood, or Quality of Life
Persistent pain can extend far beyond the painful body part.
When pain interferes with sleep, work, relationships, physical activity, or emotional well-being, these effects become part of the clinical problem and should be considered when developing a treatment plan.
This is one reason chronic pain is increasingly approached through a biopsychosocial framework rather than exclusively through structural findings or pain intensity. Multidisciplinary approaches may incorporate medical treatment, rehabilitation, lifestyle interventions, and behavioral or psychological strategies when appropriate.
You Do Not Have to Wait Until Pain Becomes Chronic
One common misconception is that pain must exist for months before someone can see a pain management physician.
That is not necessarily true.
Although pain lasting longer than three months is generally categorized as chronic, earlier evaluation can make sense when:
Recovery has stalled
Pain is repeatedly returning
Function is significantly impaired
The diagnosis remains uncertain
Neurological symptoms are developing
Appropriate conservative treatment has failed
A procedure is being considered
Symptoms are progressively worsening
The purpose of early evaluation is not to aggressively treat every injury. In many cases, the appropriate recommendation may still be conservative treatment and observation.
The difference is that those decisions are being made after evaluating the clinical picture.
When Pain Requires Urgent or Emergency Medical Care
A routine pain-management appointment is not appropriate for every painful condition.
Seek emergency or urgent medical care when pain occurs with concerning symptoms such as:
Severe trauma or suspected major fracture
Sudden weakness or paralysis
New loss of bowel or bladder control
New numbness around the groin, inner thighs, or saddle region
Chest pain or pressure
Difficulty breathing
Stroke-like symptoms such as sudden facial drooping, weakness, confusion, or difficulty speaking
A rapidly worsening swollen, red, or hot area accompanied by signs of infection
Severe pain associated with significant systemic illness
These symptoms may indicate neurological, cardiovascular, infectious, traumatic, or other urgent conditions that require immediate evaluation rather than outpatient pain treatment.
Other symptoms—including unexplained weight loss, persistent fever, a history of cancer accompanied by new unexplained pain, or pain that is progressively worsening without a clear explanation—should also prompt timely medical evaluation.
When there is uncertainty about whether symptoms may represent an emergency, it is safer to seek urgent medical assessment.
What Happens During a Pain Management Evaluation?
A thorough evaluation generally begins with conversation—not a procedure.
Your physician may ask:
When did the pain begin?
Was there an injury?
Where exactly do you feel it?
Does the pain travel?
Which movements make it better or worse?
Do you have weakness, numbness, or tingling?
What treatments have you already tried?
Have you undergone X-rays, MRI, ultrasound, or other testing?
What medications or supplements are you taking?
How has the condition affected your daily activities?
What would meaningful improvement look like for you?
A physical examination may include evaluation of range of motion, strength, tenderness, joint stability, neurological function, orthopedic testing, gait, and functional movement depending on the affected area.
Previous imaging should also be reviewed when available.
Additional testing is ordered when it is likely to change the diagnosis or treatment plan—not simply because pain exists.
You can learn more about the overall process in our Patient's Guide to Starting Integrative Pain Management.
What Treatments Might a Pain Management Physician Recommend?
There is no universal pain-management treatment.
The appropriate plan depends on the diagnosis, duration and severity of symptoms, examination findings, overall health, previous treatments, risks, goals, and patient preferences.
Depending on the situation, recommendations may include:
Activity modification
Physical therapy or rehabilitation
Progressive strengthening
Mobility exercises
Nonopioid medications when appropriate
Acupuncture
Dry needling
Trigger-point treatment
Joint or soft-tissue injections
Selected nerve procedures
Ultrasound-guided procedures
Corticosteroid injections in selected cases
Prolotherapy or platelet-rich plasma for selected musculoskeletal conditions
Lifestyle or recovery strategies
Referral to orthopedics, neurology, rheumatology, physical medicine and rehabilitation, surgery, or another appropriate specialist
Evidence differs substantially between conditions and treatments, particularly for regenerative procedures. A treatment that may be appropriate for one tendon or joint condition may provide little benefit for another.
That is why Ask Dr. Hu's integrative pain management approach emphasizes selecting treatments after an individualized evaluation rather than using the same protocol for everyone.
Does Seeing a Pain Management Physician Mean You Will Need an Injection?
No.
A pain-management evaluation and a pain procedure are two different things.
Many patients may appropriately be treated with rehabilitation, exercise, activity modification, medication, acupuncture, or other conservative approaches. Other patients may benefit from additional diagnostic evaluation or referral.
Procedures are considered when the suspected diagnosis, expected benefits, limitations, risks, alternatives, and patient's treatment goals make them reasonable.
A physician should be able to explain why a proposed procedure is being recommended before you decide whether to proceed.
Should You See Primary Care or Pain Management First?
Either may be appropriate depending on the situation.
Primary care physicians can evaluate and manage many common acute and chronic painful conditions. A more focused pain-management evaluation may become useful when the diagnosis is uncertain, symptoms persist despite treatment, function remains significantly limited, specialized diagnostic evaluation is needed, or procedural treatment is being considered.
Some patients also require coordination among multiple healthcare professionals. Chronic pain care may involve primary care, rehabilitation professionals, pain clinicians, neurologists, orthopedic specialists, behavioral health professionals, pharmacists, and other disciplines depending on the condition.
The objective should be coordinated care—not simply accumulating more treatments.
How to Choose a Pain Management Physician
When considering a pain-management practice, look beyond the list of procedures offered.
A thoughtful clinician should be willing to:
Review your medical history and previous treatment
Perform an appropriate physical examination
Discuss the likely diagnosis
Explain when additional testing is or is not necessary
Consider conservative treatment
Explain reasonable treatment alternatives
Discuss potential benefits and limitations
Review important risks before procedures
Set realistic expectations
Consider your functional goals
Refer elsewhere when another specialist is more appropriate
Be cautious when a specific injection or procedure is recommended before the clinician has adequately evaluated the problem.
The question should not simply be, "What can we inject?"
It should be, "What is most likely causing the pain, and what is the most appropriate next step?"
When to Consider an Integrative Pain Management Evaluation at Ask Dr. Hu
If you are experiencing persistent, recurring, or function-limiting muscle, tendon, joint, nerve, back, neck, or other musculoskeletal pain, an individualized evaluation may help clarify your options.
Ask Dr. Hu provides integrative pain management in Arizona, with care that may include conservative treatment recommendations, rehabilitation planning, acupuncture, dry needling, diagnostic musculoskeletal ultrasound, ultrasound-guided procedures, targeted injections, and selected regenerative treatments when clinically appropriate.
You can also explore the Integrative Pain Management Resource Center for physician-written information about diagnosis, rehabilitation, musculoskeletal ultrasound, regenerative medicine, and personalized pain treatment.
Frequently Asked Questions
Do I have to be in pain for three months before seeing a pain management physician?
No. Three months is commonly used to distinguish chronic pain from shorter-duration pain, but evaluation may be appropriate earlier when recovery has stalled, pain is recurring, function is impaired, neurological symptoms are present, or the diagnosis is uncertain.
Does seeing a pain management physician mean I will need injections?
No. Many patients may benefit from conservative treatment, rehabilitation, exercise, medications, acupuncture, or other approaches. Procedures should be selected only when they are appropriate for the diagnosis and individual patient.
What should I bring to my first pain-management appointment?
Bring a current medication and supplement list, relevant medical records, previous imaging reports or images if available, information about previous treatments, and a clear description of how the pain affects your daily activities. This can help your physician understand what has already been evaluated and what questions remain.
Can a pain management physician help if my MRI did not show anything serious?
Possibly. Imaging is only one component of a musculoskeletal evaluation. Symptoms, physical examination findings, neurological testing, functional limitations, and the relationship between imaging findings and the patient's symptoms all matter when determining the likely source of pain.
Medical References and Editorial Standards
This article was developed for patient education using established clinical guidance and evidence-informed principles of pain evaluation and treatment.
Key references include the CDC Clinical Practice Guideline for Prescribing Opioids for Pain, the CDC's guidance on working with your doctor to manage pain, the American Academy of Family Physicians Chronic Pain Toolkit, and peer-reviewed literature describing the role of multidisciplinary care in pain management.
Medical evidence evolves, and treatment recommendations should always be individualized according to a patient's diagnosis, medical history, examination findings, treatment goals, and clinical circumstances.
About the Author
YiQiu Hu, NMD, is an Arizona-licensed naturopathic physician, founder of Ask Dr. Hu, and medical director with experience in personalized and multidisciplinary healthcare. His clinical interests include preventive medicine, health optimization, hormone care, laboratory evaluation, integrative pain management, medical weight management, and the ongoing management of complex health concerns.
Learn more about Dr. Hu and the physicians at Ask Dr. Hu.
Medical Disclaimer: This article is intended for general educational purposes and does not replace individualized medical evaluation, diagnosis, or treatment. Pain-management services are not appropriate substitutes for emergency care. Seek immediate medical attention for severe trauma, sudden weakness or paralysis, new bowel or bladder dysfunction, chest pain, difficulty breathing, stroke-like symptoms, or other potentially serious symptoms.
Experiencing persistent or recurring musculoskeletal pain?
Explore Integrative Pain Management or contact Ask Dr. Hu to discuss whether an evaluation may be appropriate.